

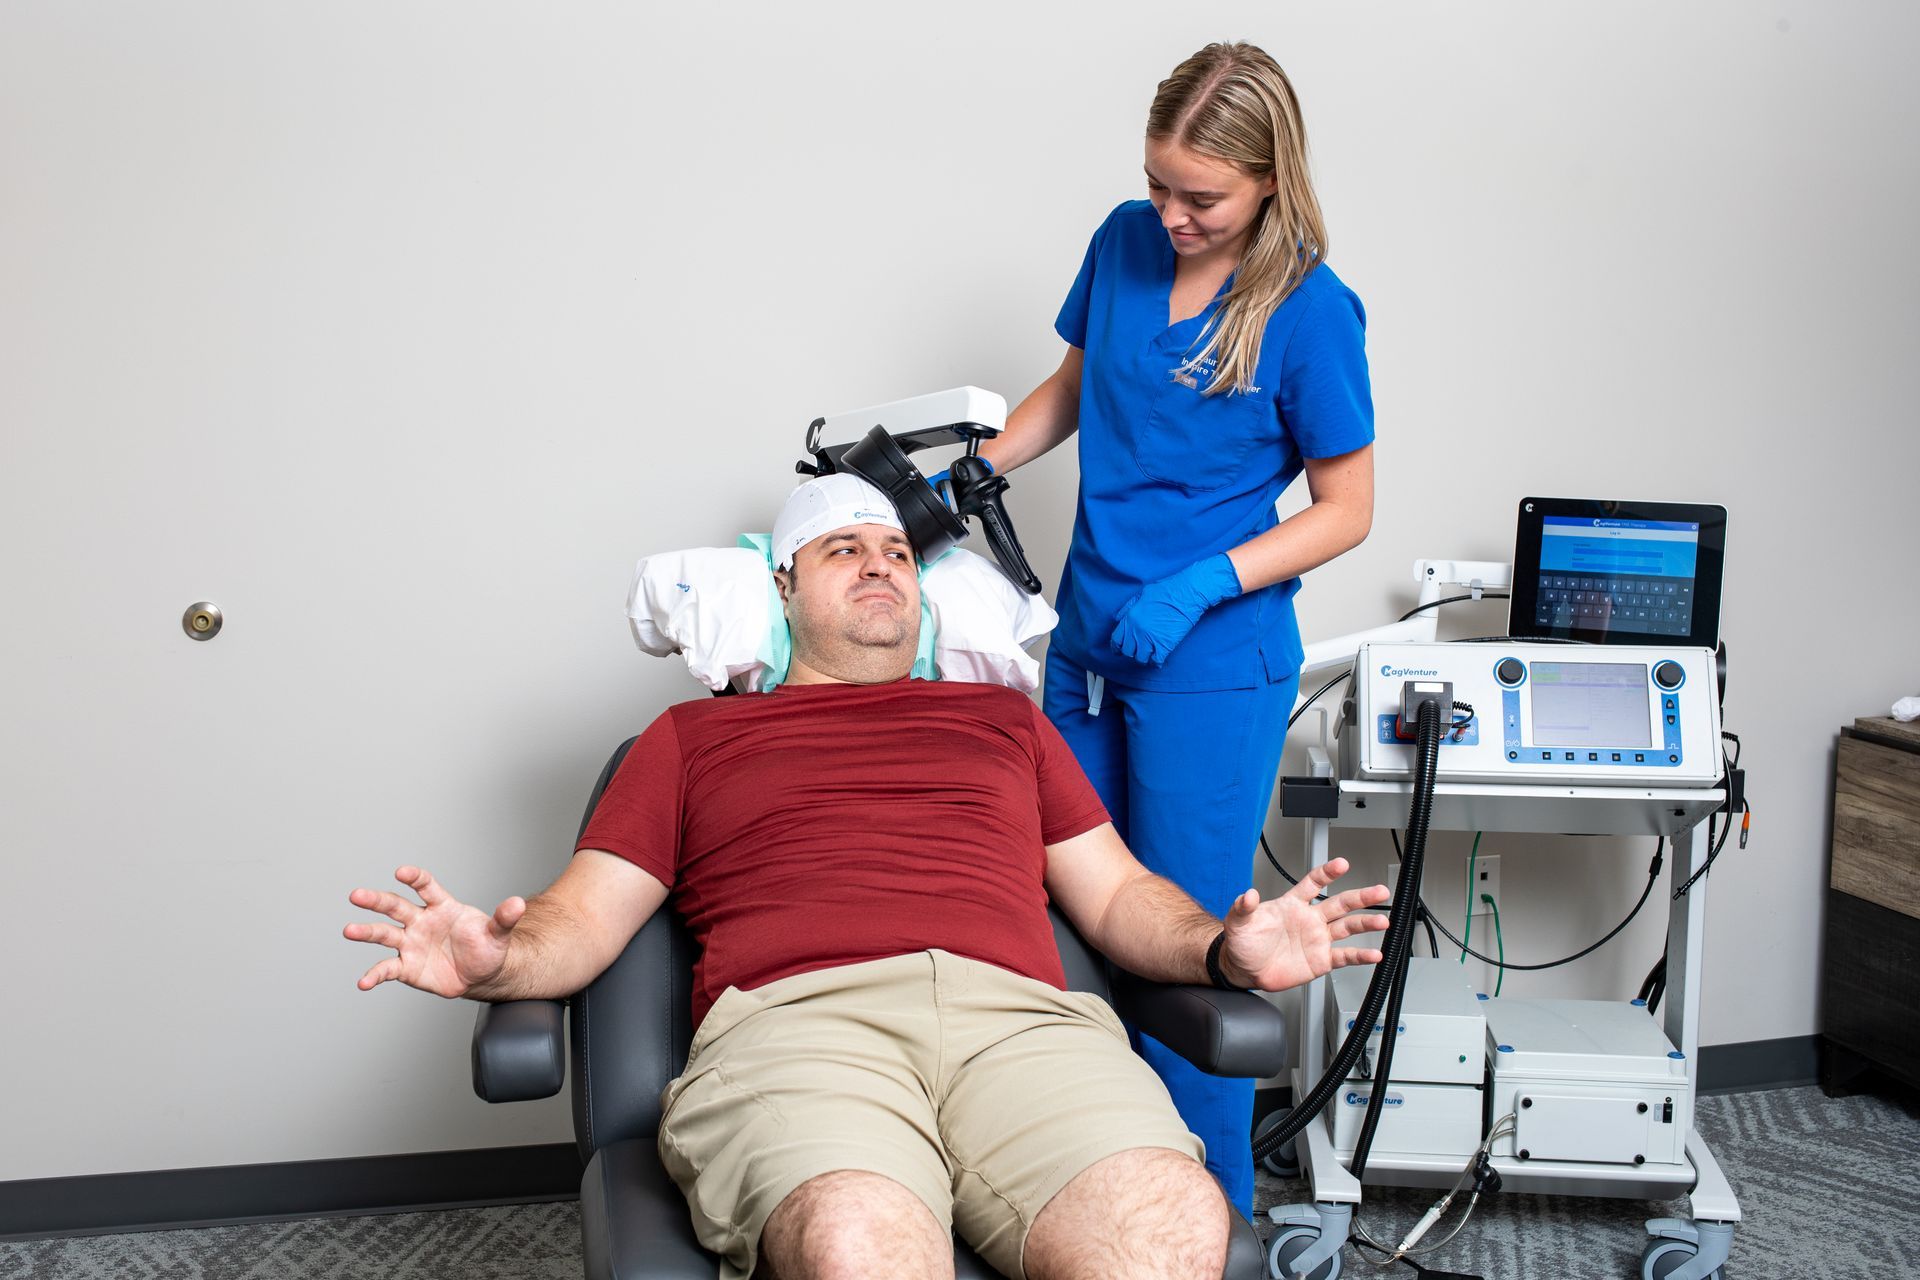





Depression during pregnancy is common and serious, and for mothers who want to avoid exposing their baby to medication, TMS is worth knowing about. It's a no...
If you've tried two or more antidepressants without lasting relief, you're not out of options, you've reached the point where it's worth looking beyond anoth...

Anxious depression is depression that comes with significant anxiety, the racing mind, the restlessness, the dread, on top of the low mood. It's common, it t...

Stopped antidepressants because of the side effects? TMS avoids the systemic effects, weight gain, low libido, numbness, that make medication hard to tolerate.
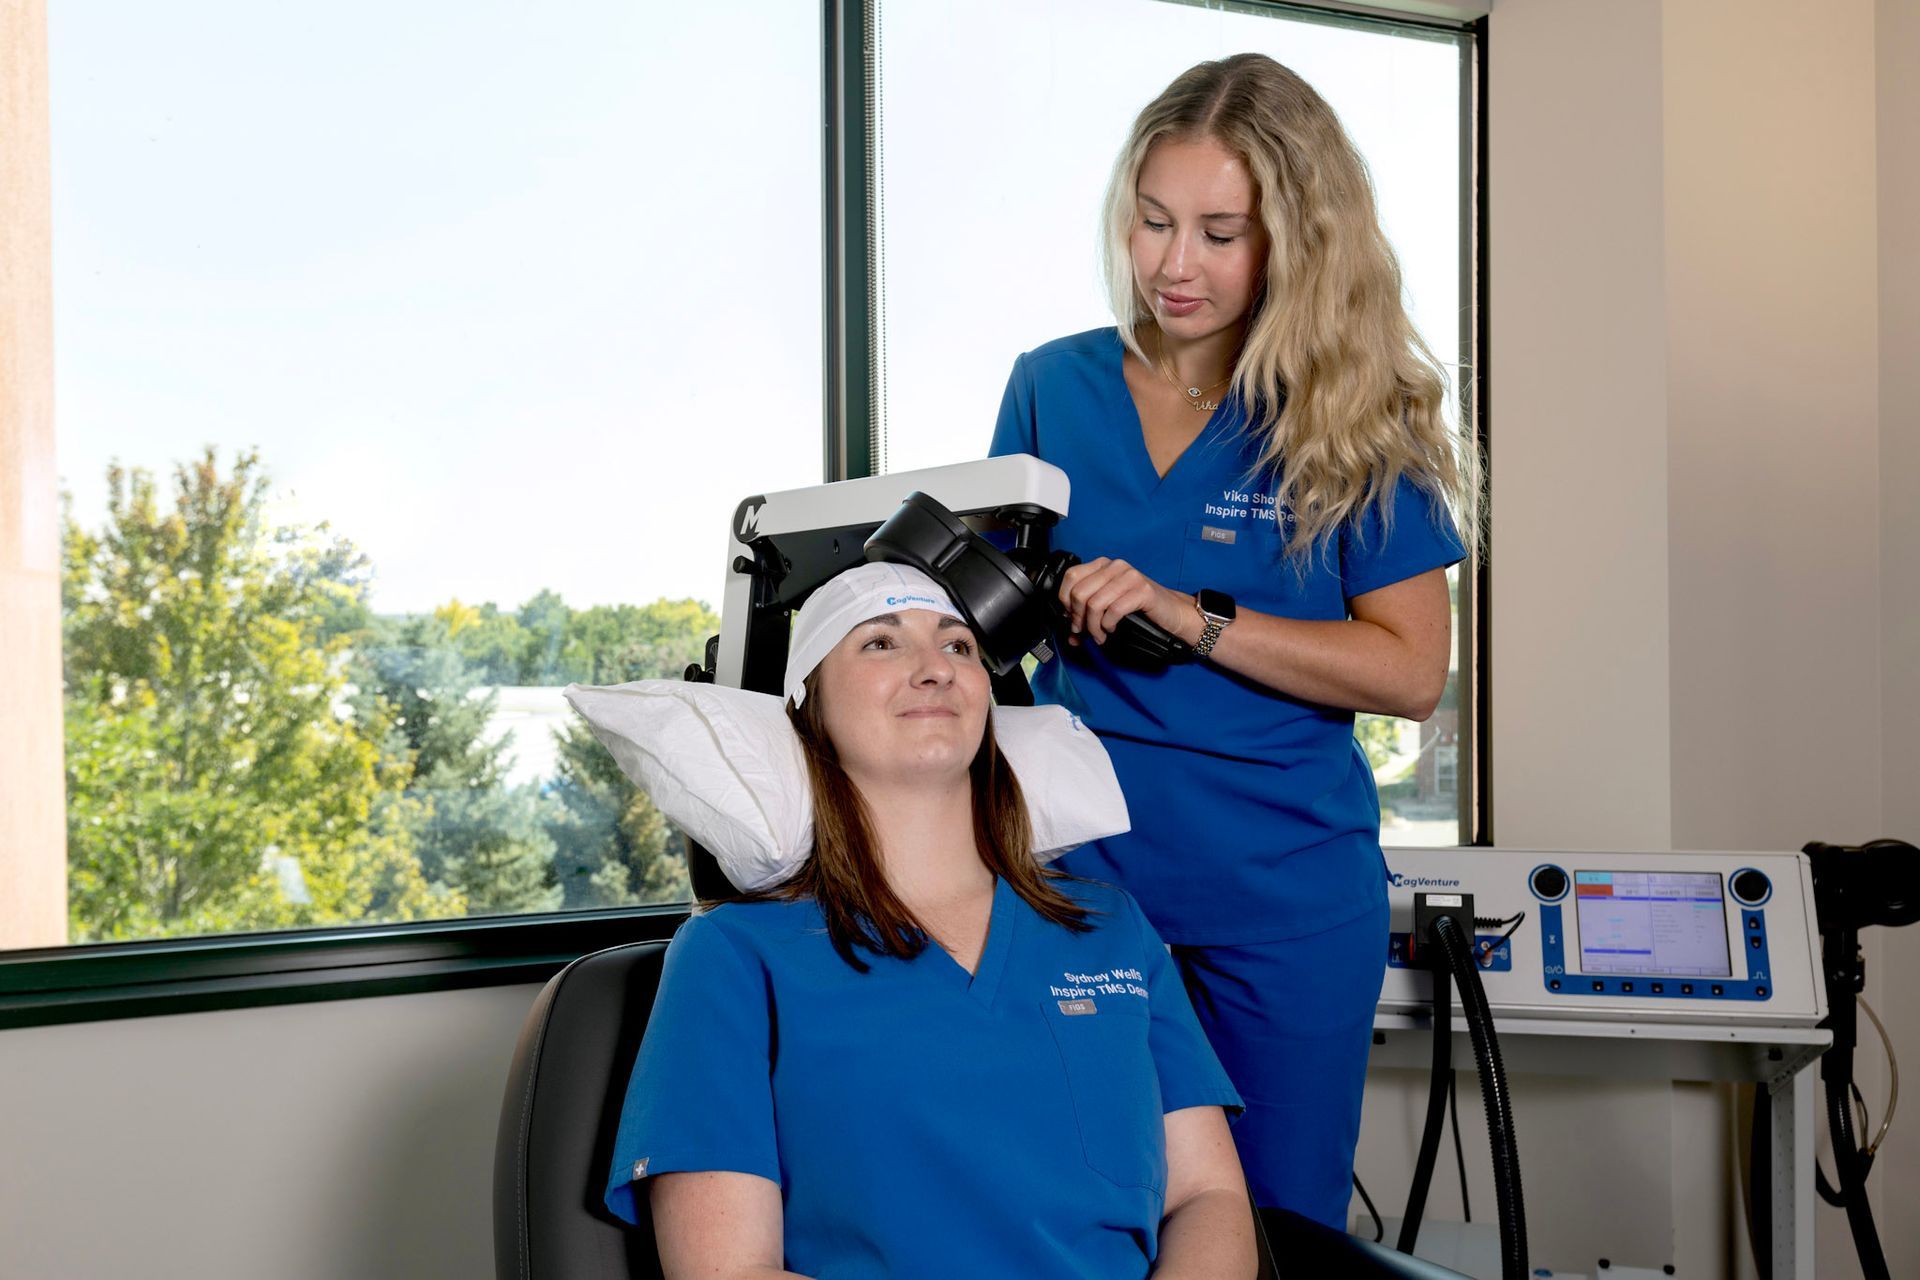
Tried two or more antidepressants without relief? TMS is FDA-cleared for exactly that. An honest look at how it works when medication hasn't, and who it's for.

Does TMS cause weight gain? No. It's weight-neutral, unlike many antidepressants. Here's the honest reason why, and what any weight change during treatment means.
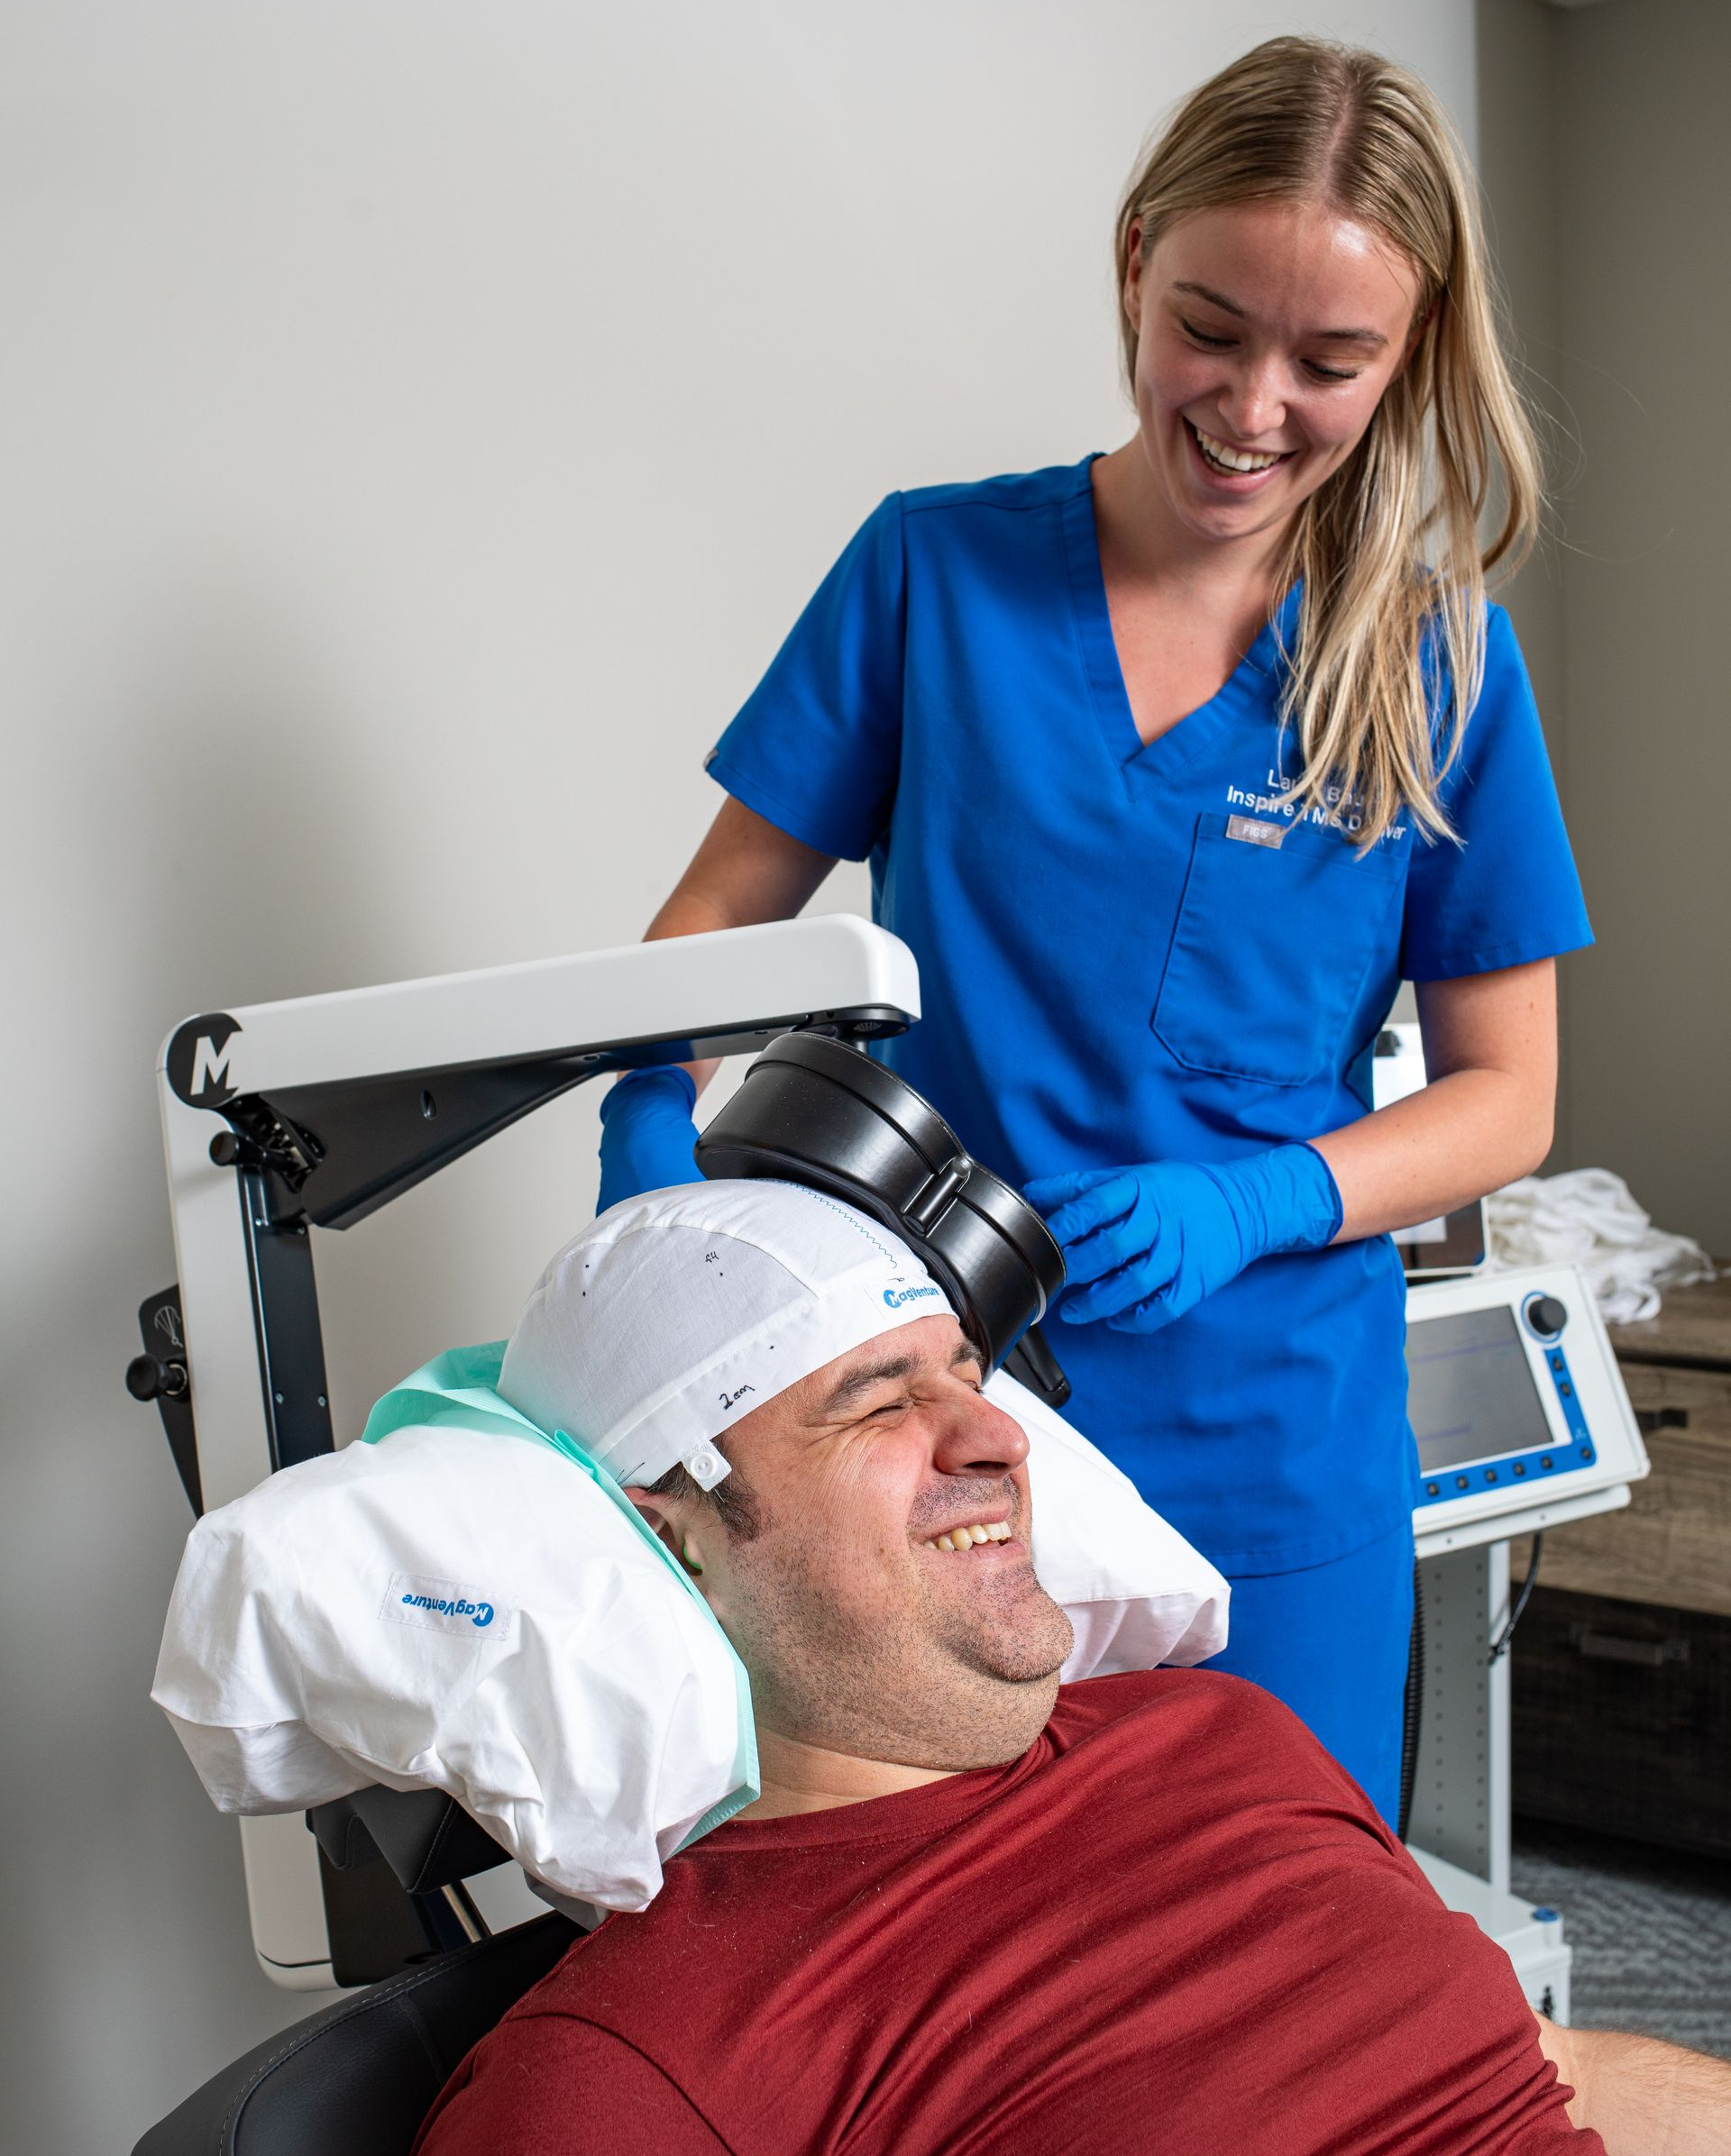
Does TMS affect memory? No, it's not linked to lasting memory loss, and it isn't ECT. Here's the honest picture, including why your focus may actually improve.

Is TMS safe? A straight look at the real side effects, the rare serious risks, and the truth behind "TMS ruined my life" stories, so you can decide clearly.

Quick Answer: Yes. TriCare covers TMS for adults with major depressive disorder on an outpatient basis. TriCare is accepted at Inspire TMS Denver, and your benefits are checked before treatment begins so you know your costs up front. TMS is FDA-cleared for depression, and if antidepressants have not worked, it may be a covered next step. Depression is common in the military community, and it often travels alongside the other things service members and their families carry, including PTSD and anxiety. If medication has not brought the relief you were hoping for, TMS is worth understanding, and for TriCare beneficiaries it is a covered option. What Is TMS Therapy? TMS (transcranial magnetic stimulation) is a non-invasive, FDA-cleared treatment for depression. It uses targeted magnetic pulses to stimulate the areas of the brain involved in mood regulation. There is no anesthesia and no sedation. Most people drive themselves to and from sessions and go straight back to their day. It is usually considered when antidepressant medications have not provided enough relief, which is also the point at which TriCare coverage becomes relevant. Does TriCare Cover TMS? Yes, for major depressive disorder . TriCare covers TMS as an outpatient treatment for adults with major depressive disorder. TriCare is accepted at Inspire TMS Denver. Coverage still depends on your specific plan and on the documentation your provider submits, so it is not something to guess at. Rather than have you work it out alone, the clinic verifies your benefits before treatment begins and gives you an estimate of any out-of-pocket cost, so there are no surprises once you start. PTSD, Depression, and What TriCare Actually Covers This is the part worth being straight about, because it affects whether your treatment gets approved. TMS is FDA-cleared and TriCare-covered for major depressive disorder. It is not covered as a standalone treatment for PTSD. A lot of people in the military community come in thinking of PTSD as the main issue, and depression is very often part of that same picture. Where major depressive disorder is present and documented, that is the diagnosis that opens the door to TMS coverage. You do not need to untangle this yourself. During your evaluation, the clinical team determines the correct primary diagnosis and handles the paperwork that goes to TriCare. What helps most is being open about your full history, including your mood, your medication trials, and what has and has not worked. Who Does TriCare Cover? TriCare serves active duty service members, activated National Guard and Reserve members, military retirees, and their families. If you are a veteran who separated without retiring, your coverage may run through the VA rather than TriCare, which is a different pathway. If you are not sure which applies to you, the screening call is the fastest way to find out where you stand.
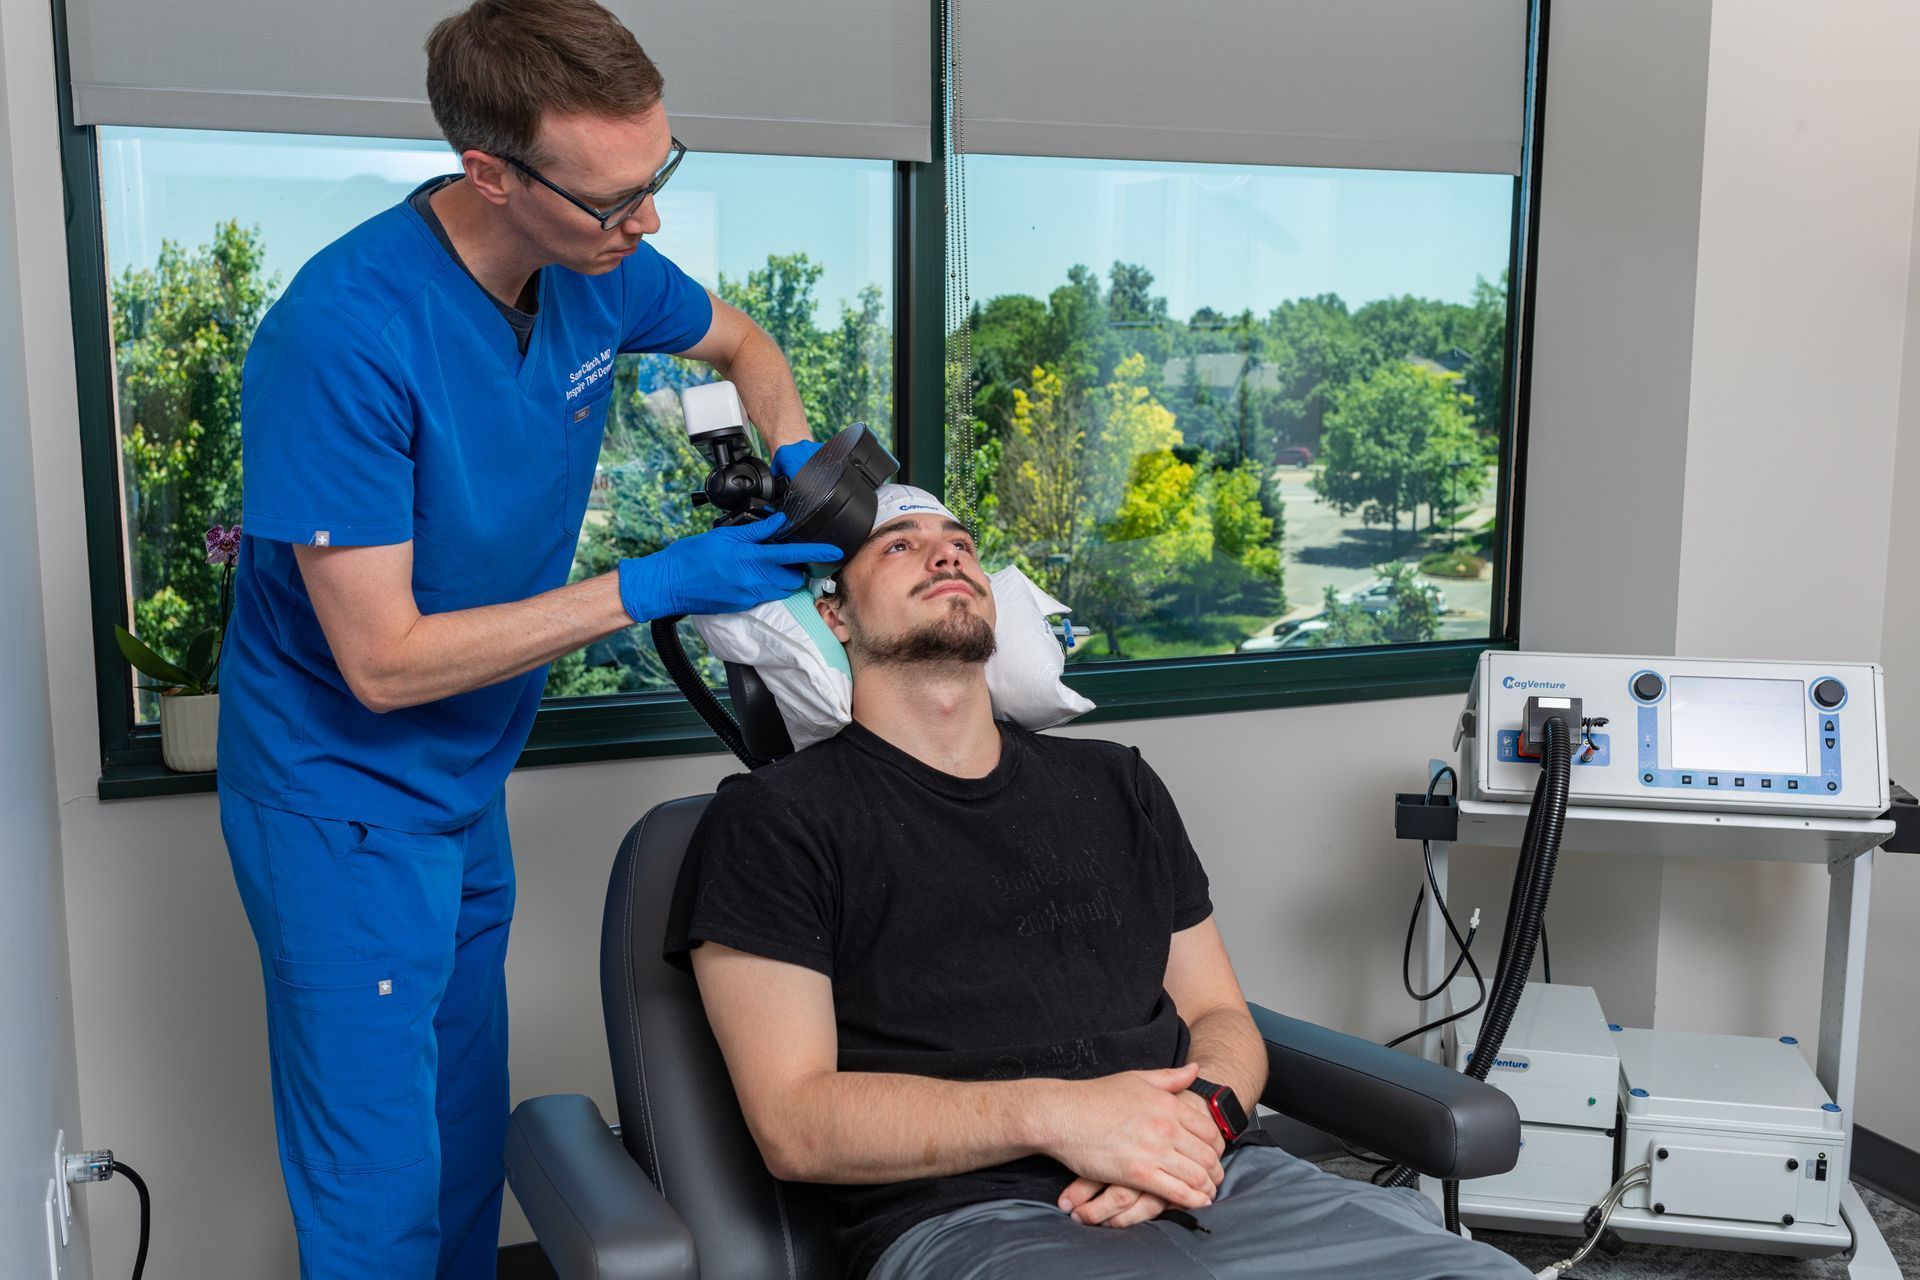
Quick Answer: As of August 2025, TMS is FDA-cleared for adolescents aged 15 to 21 with major depressive disorder, as an add-on (adjunct) to antidepressant medication for teens who haven't responded adequately to medication alone. It's non-invasive, drug-free, and done without sedation. It is not a replacement for medication or therapy, and at our clinic, a teen must have an existing psychiatrist and therapist to begin. This post explains what the clearance actually covers, what treatment involves, and how to tell if it's worth exploring for your child. If your teenager has been struggling with depression and medication hasn't been enough, you've probably reached the point of asking what else exists. TMS is now a real, FDA-cleared option for adolescents, but there's a lot of loose language online about what it is and who it's for. Here's the accurate version, written for parents who want the facts without the hype. Is TMS FDA-Cleared for Teenagers? Yes, with specific limits worth understanding. In August 2025, the FDA cleared the MagVenture TMS system , the equipment we use, as an adjunct treatment for major depressive disorder in adolescent patients aged 15 to 21. (Other manufacturers received similar adolescent clearances around the same period.) Two details matter here, because a lot of websites blur them: It's FDA-cleared, not "FDA-approved." Those are different regulatory pathways, and cleared is the correct term for TMS devices. The clearance covers ages 15 to 21, not an open-ended "15 and up." There's a defined upper bound. We're precise about this because when the topic is treating a minor, the details are the whole point. What "Adjunct" Actually Means This is the part most worth understanding. The FDA cleared TMS for adolescents as an adjunct, which means an add-on used alongside antidepressant medication, for teens who have not responded adequately to that medication on its own. It is not cleared as a replacement for medication, and the evidence in adolescents is strongest when TMS is added to an existing antidepressant rather than used by itself. So the honest framing is this: TMS is a way to boost the effect of treatment your teen is already on when that treatment hasn't been enough, not a way to take them off their medication. Any clinic suggesting TMS can simply replace a teenager's antidepressant is getting ahead of what the science and the clearance actually support. How TMS Works and What Treatment Involves TMS uses targeted magnetic pulses to stimulate a region of the brain involved in mood regulation, the left dorsolateral prefrontal cortex. It's non-invasive: nothing enters the body, there's no sedation or anesthetic, and your teen is fully awake throughout. Practically, for your child that means: Short daily sessions. Treatment sessions run about 18.5 minutes, with patients typically in and out of the office within half an hour. A weekday schedule. A standard course runs daily on weekdays over about six weeks, followed by a short taper of two to three weeks. No downtime. Because there's no sedation, teens can return to school and normal activities immediately after each session. Generally mild side effects. When they occur, side effects are usually localized: some scalp discomfort at the treatment site during the pulses, which typically stops as soon as the session ends, and occasional headaches that usually respond to over-the-counter pain relief. Often there are no side effects at all. TMS does not involve the sedation or systemic medication effects that come with some other treatments, and it is not associated with effects on memory or concentration. Why Consider TMS for a Teen? Adolescence is a period when depression often appears for the first time, and standard treatments don't always work. Some teens don't respond to the medications they try; others struggle with side effects or find it hard to stay on medication consistently. When that's the situation, a non-drug option that adds to their existing care can be genuinely valuable. That's the role TMS plays here: another tool for teens whose depression hasn't lifted enough with medication and therapy alone, not a first move and not a standalone fix.




