







Does TMS cause weight gain? No. It's weight-neutral, unlike many antidepressants. Here's the honest reason why, and what any weight change during treatment means.
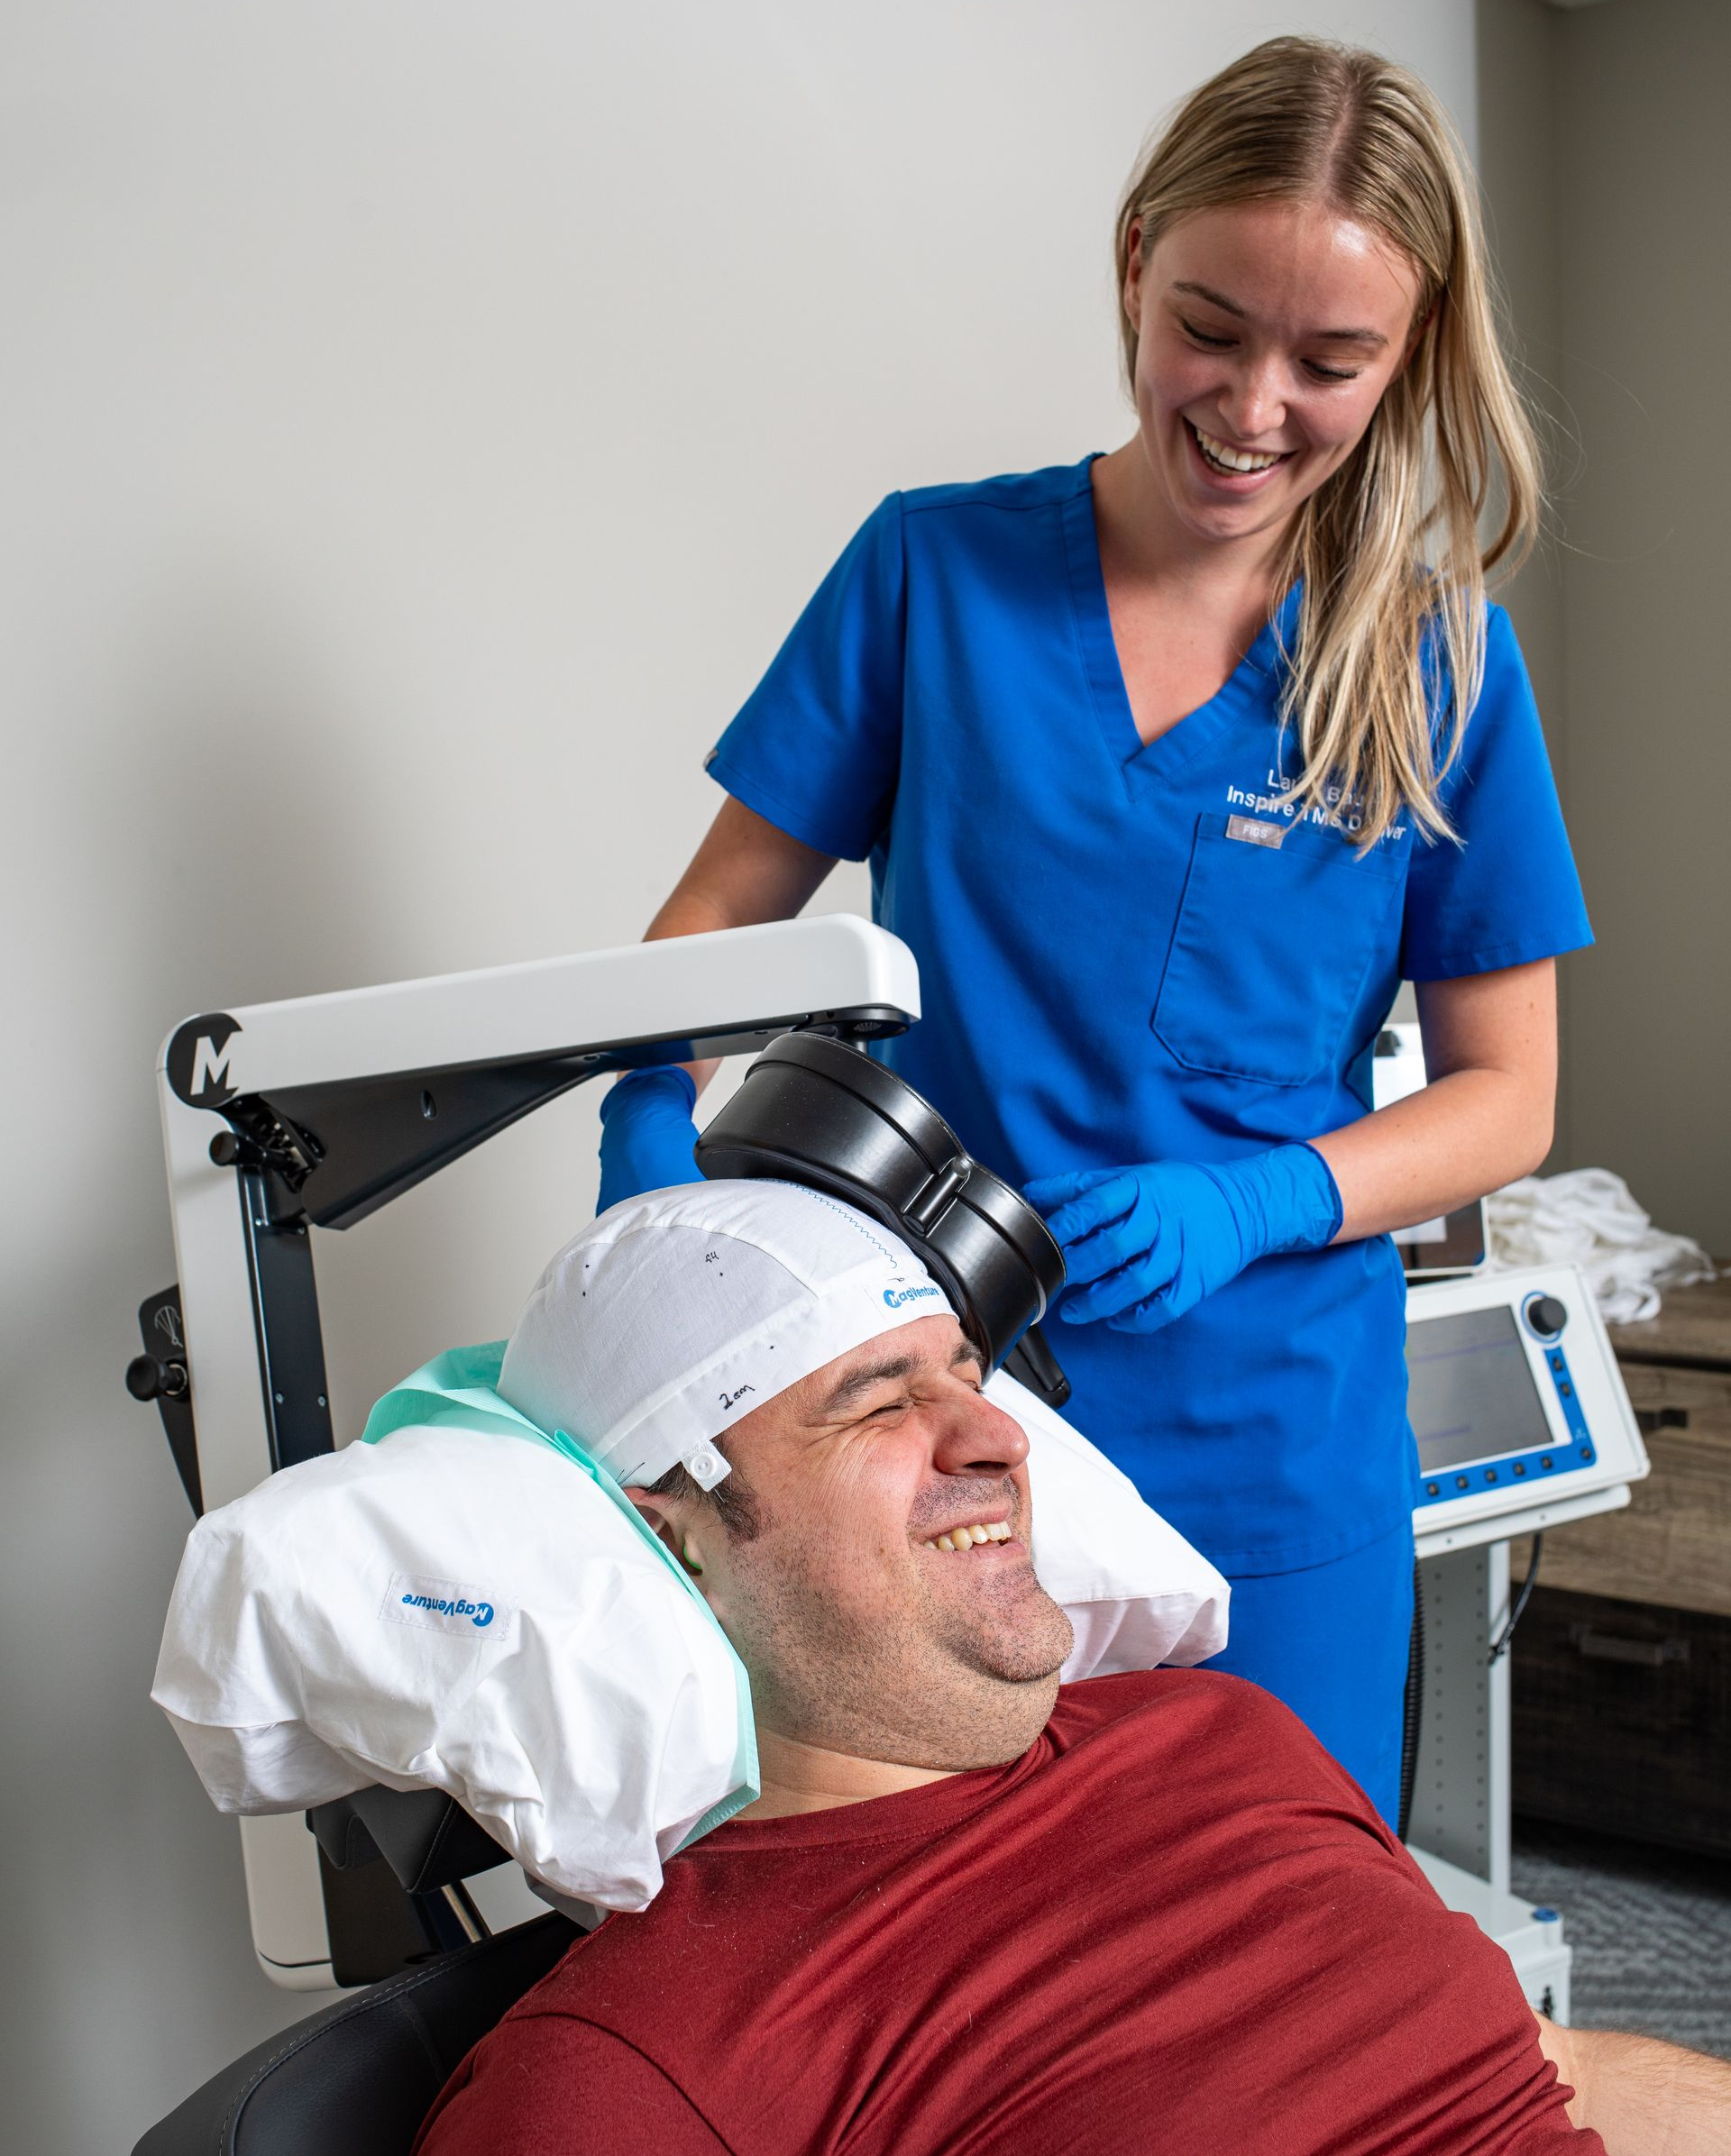
Does TMS affect memory? No, it's not linked to lasting memory loss, and it isn't ECT. Here's the honest picture, including why your focus may actually improve.

Quick Answer: Yes. TriCare covers TMS for adults with major depressive disorder on an outpatient basis. TriCare is accepted at Inspire TMS Denver, and your benefits are checked before treatment begins so you know your costs up front. TMS is FDA-cleared for depression, and if antidepressants have not worked, it may be a covered next step. Depression is common in the military community, and it often travels alongside the other things service members and their families carry, including PTSD and anxiety. If medication has not brought the relief you were hoping for, TMS is worth understanding, and for TriCare beneficiaries it is a covered option. What Is TMS Therapy? TMS (transcranial magnetic stimulation) is a non-invasive, FDA-cleared treatment for depression. It uses targeted magnetic pulses to stimulate the areas of the brain involved in mood regulation. There is no anesthesia and no sedation. Most people drive themselves to and from sessions and go straight back to their day. It is usually considered when antidepressant medications have not provided enough relief, which is also the point at which TriCare coverage becomes relevant. Does TriCare Cover TMS? Yes, for major depressive disorder . TriCare covers TMS as an outpatient treatment for adults with major depressive disorder. TriCare is accepted at Inspire TMS Denver. Coverage still depends on your specific plan and on the documentation your provider submits, so it is not something to guess at. Rather than have you work it out alone, the clinic verifies your benefits before treatment begins and gives you an estimate of any out-of-pocket cost, so there are no surprises once you start. PTSD, Depression, and What TriCare Actually Covers This is the part worth being straight about, because it affects whether your treatment gets approved. TMS is FDA-cleared and TriCare-covered for major depressive disorder. It is not covered as a standalone treatment for PTSD. A lot of people in the military community come in thinking of PTSD as the main issue, and depression is very often part of that same picture. Where major depressive disorder is present and documented, that is the diagnosis that opens the door to TMS coverage. You do not need to untangle this yourself. During your evaluation, the clinical team determines the correct primary diagnosis and handles the paperwork that goes to TriCare. What helps most is being open about your full history, including your mood, your medication trials, and what has and has not worked. Who Does TriCare Cover? TriCare serves active duty service members, activated National Guard and Reserve members, military retirees, and their families. If you are a veteran who separated without retiring, your coverage may run through the VA rather than TriCare, which is a different pathway. If you are not sure which applies to you, the screening call is the fastest way to find out where you stand.
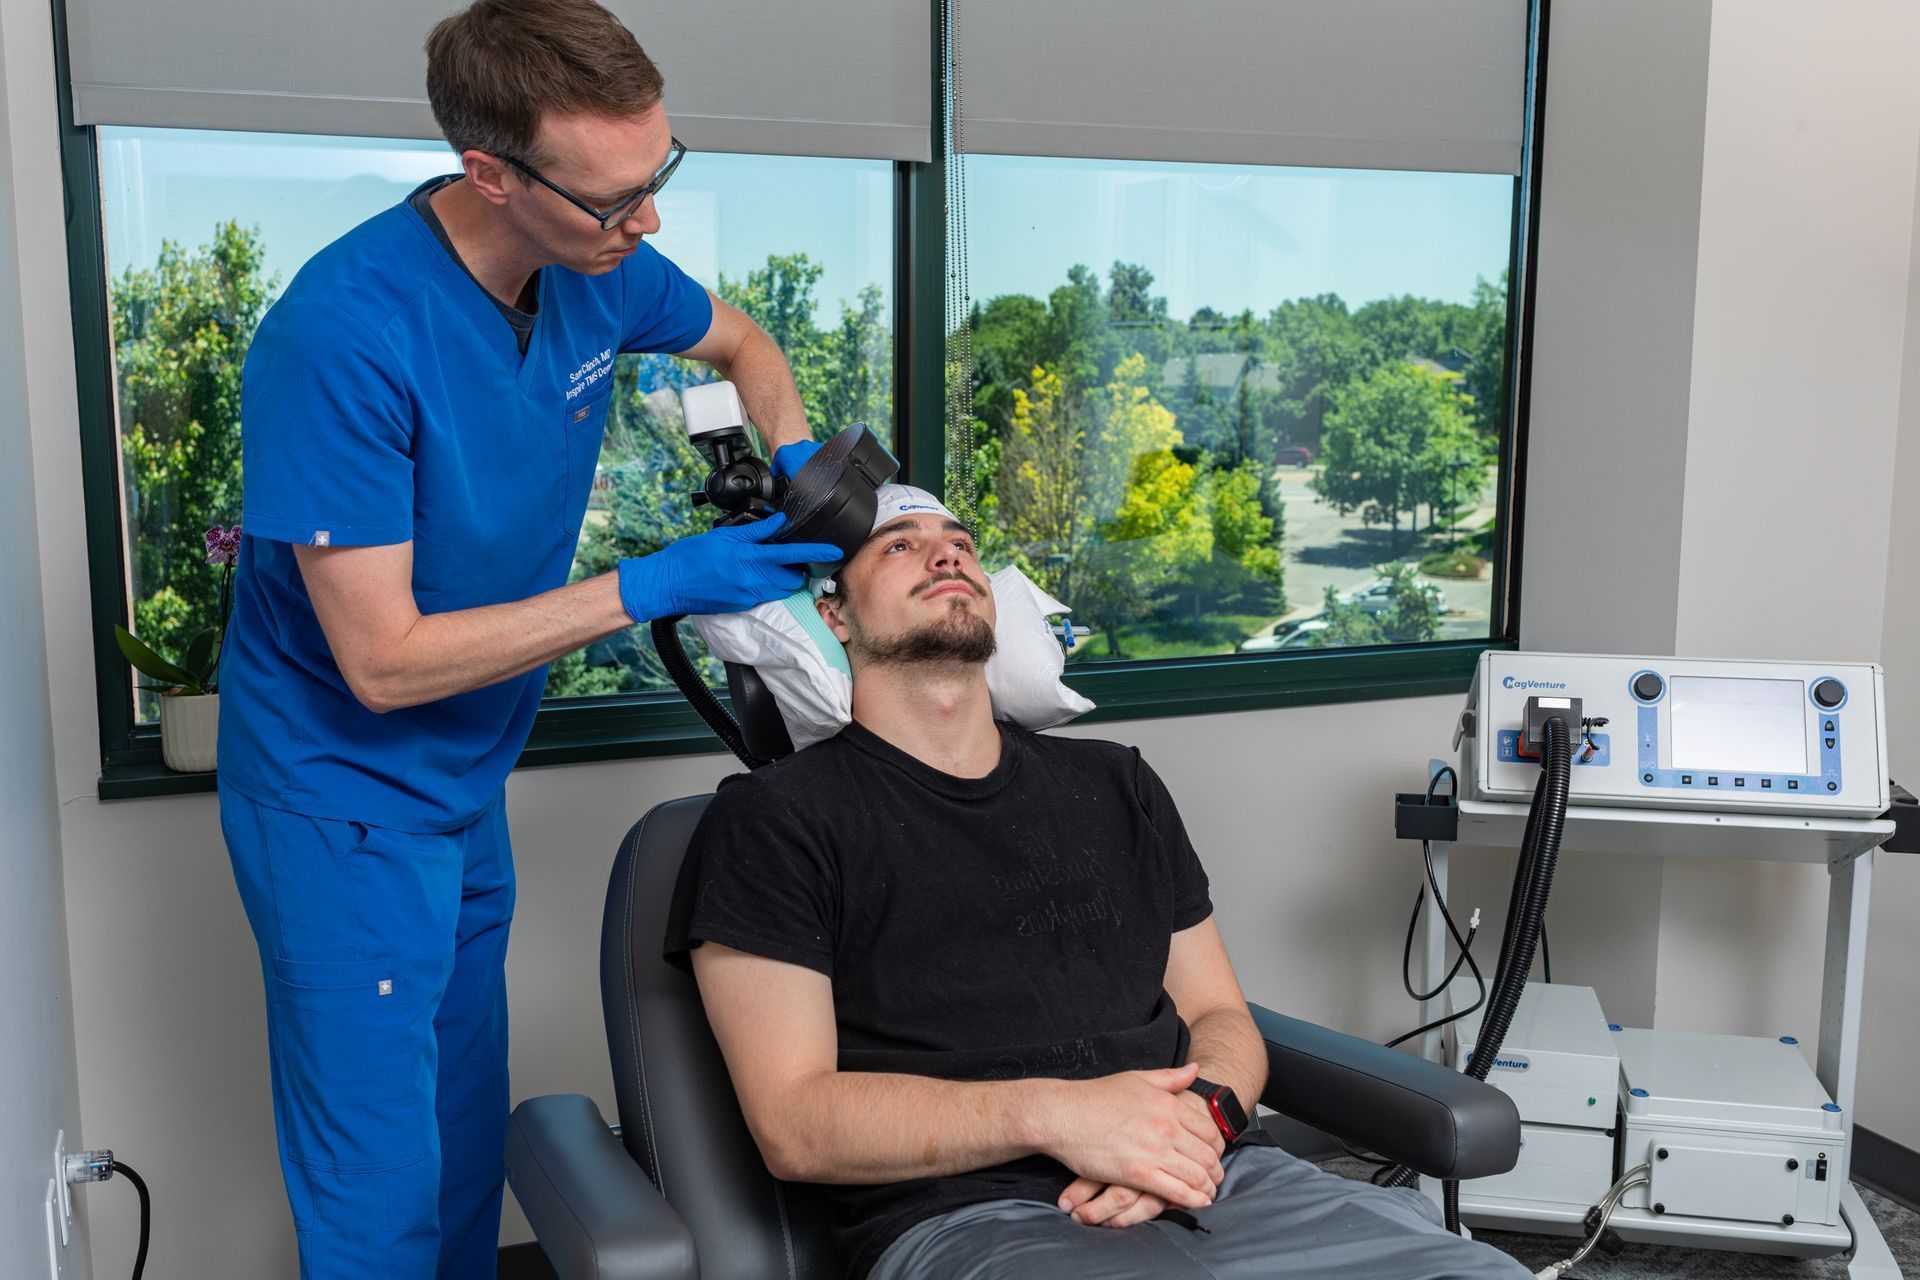
Quick Answer: As of August 2025, TMS is FDA-cleared for adolescents aged 15 to 21 with major depressive disorder, as an add-on (adjunct) to antidepressant medication for teens who haven't responded adequately to medication alone. It's non-invasive, drug-free, and done without sedation. It is not a replacement for medication or therapy, and at our clinic, a teen must have an existing psychiatrist and therapist to begin. This post explains what the clearance actually covers, what treatment involves, and how to tell if it's worth exploring for your child. If your teenager has been struggling with depression and medication hasn't been enough, you've probably reached the point of asking what else exists. TMS is now a real, FDA-cleared option for adolescents, but there's a lot of loose language online about what it is and who it's for. Here's the accurate version, written for parents who want the facts without the hype. Is TMS FDA-Cleared for Teenagers? Yes, with specific limits worth understanding. In August 2025, the FDA cleared the MagVenture TMS system , the equipment we use, as an adjunct treatment for major depressive disorder in adolescent patients aged 15 to 21. (Other manufacturers received similar adolescent clearances around the same period.) Two details matter here, because a lot of websites blur them: It's FDA-cleared, not "FDA-approved." Those are different regulatory pathways, and cleared is the correct term for TMS devices. The clearance covers ages 15 to 21, not an open-ended "15 and up." There's a defined upper bound. We're precise about this because when the topic is treating a minor, the details are the whole point. What "Adjunct" Actually Means This is the part most worth understanding. The FDA cleared TMS for adolescents as an adjunct, which means an add-on used alongside antidepressant medication, for teens who have not responded adequately to that medication on its own. It is not cleared as a replacement for medication, and the evidence in adolescents is strongest when TMS is added to an existing antidepressant rather than used by itself. So the honest framing is this: TMS is a way to boost the effect of treatment your teen is already on when that treatment hasn't been enough, not a way to take them off their medication. Any clinic suggesting TMS can simply replace a teenager's antidepressant is getting ahead of what the science and the clearance actually support. How TMS Works and What Treatment Involves TMS uses targeted magnetic pulses to stimulate a region of the brain involved in mood regulation, the left dorsolateral prefrontal cortex. It's non-invasive: nothing enters the body, there's no sedation or anesthetic, and your teen is fully awake throughout. Practically, for your child that means: Short daily sessions. Treatment sessions run about 18.5 minutes, with patients typically in and out of the office within half an hour. A weekday schedule. A standard course runs daily on weekdays over about six weeks, followed by a short taper of two to three weeks. No downtime. Because there's no sedation, teens can return to school and normal activities immediately after each session. Generally mild side effects. When they occur, side effects are usually localized: some scalp discomfort at the treatment site during the pulses, which typically stops as soon as the session ends, and occasional headaches that usually respond to over-the-counter pain relief. Often there are no side effects at all. TMS does not involve the sedation or systemic medication effects that come with some other treatments, and it is not associated with effects on memory or concentration. Why Consider TMS for a Teen? Adolescence is a period when depression often appears for the first time, and standard treatments don't always work. Some teens don't respond to the medications they try; others struggle with side effects or find it hard to stay on medication consistently. When that's the situation, a non-drug option that adds to their existing care can be genuinely valuable. That's the role TMS plays here: another tool for teens whose depression hasn't lifted enough with medication and therapy alone, not a first move and not a standalone fix.

Quick Answer: A TMS assessment is a psychiatric evaluation, not a treatment session. You'll sit down with Dr. Clinch to go through your history, your current symptoms, and what you've already tried, and he'll screen for the safety factors that determine whether TMS is appropriate for you . You'll also complete baseline symptom scoring and go through the practical side: insurance, cost, and scheduling. Nothing is done to you that day, and there's no obligation to proceed. This post walks through exactly what to expect. Booking a first appointment for something you've never done is uncomfortable when you don't know what it involves. A TMS assessment is straightforward and low-pressure, but "assessment" can sound clinical and vague. Here's a plain account of what actually happens, start to finish. Who You'll See Your assessment is with Dr. Samuel Clinch, a board-certified psychiatrist and the clinic's founder. This matters more than it might sound. At a lot of clinics, the first person you meet is a coordinator or a technician, and the doctor comes later, if at all. Here, the clinical evaluation is done by the psychiatrist who will oversee your care, because deciding whether TMS is right for you is a medical judgment, not an intake form. That also means you can ask real questions and get real answers in the room, rather than being handed a brochure and a follow-up number. The Conversation: Your History and Symptoms The core of the assessment is a proper conversation about what's brought you here. Expect to cover: What you're experiencing now. Your symptoms, how long they've been going on, and how they affect your day-to-day life. What you've already tried. Medications, therapy, other treatments, and how you responded to each. TMS is often considered when medication hasn't given full relief, so this history genuinely shapes the recommendation. Your medical and psychiatric background. Diagnoses, relevant health conditions, and current medications. What you're hoping for. Realistic goals matter, and they help set expectations for what treatment can and can't do. You'll also complete baseline symptom scoring, usually the PHQ-9 for depression or the GAD-7 for anxiety. These give a fixed starting point, so that if you go ahead with treatment, improvement is measured against where you began rather than estimated from memory. The Safety Screening TMS is well tolerated , but it isn't suitable for everyone, and part of the assessment is a careful safety screen. This is where seemingly small questions carry weight. Dr. Clinch will check for things like a history of seizures, significant head injury, and any magnetically sensitive implants or metal above the neck, since the treatment uses magnetic pulses. He'll also screen for conditions such as bipolar disorder, because that affects how treatment is approached. If some of the intake questions feel unrelated to your mood, this is why. They're there to make sure treatment is safe and appropriate for you specifically, and they're not a formality.
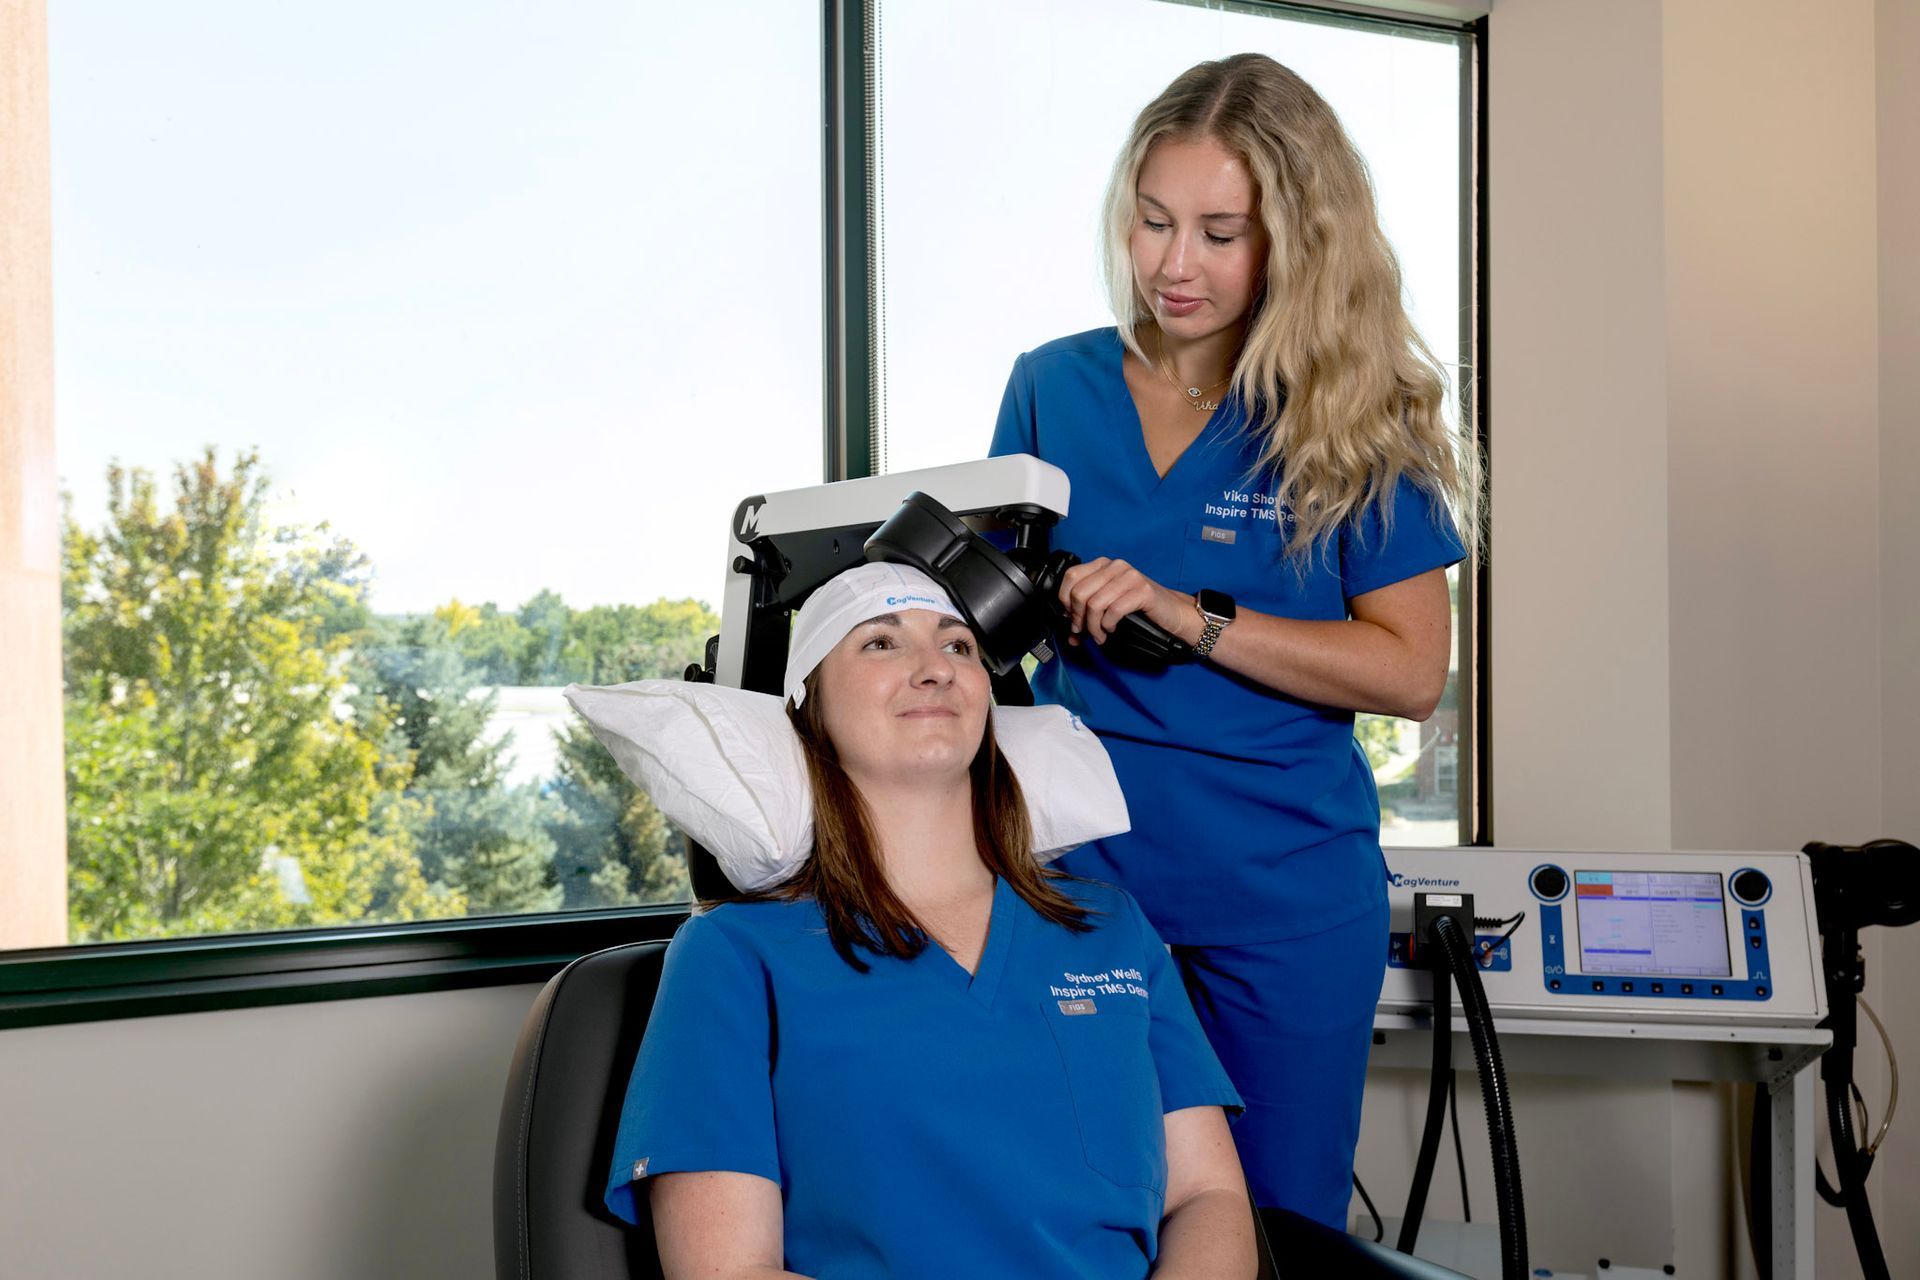
Quick Answer: Improvement from TMS is usually gradual, not a switch that flips. Most people start noticing change in the middle of a course, often between sessions 20 and 30, not after the first session. It's measured on real symptom scales, and it comes in two levels: a response (symptoms at least halved) and remission (no longer scoring as depressed). This post sets honest expectations about what changes, when, and how it's actually measured, using our own tracked results rather than generic claims. Most content about TMS results falls into one of two traps: vague promises ("feel like yourself again") or cherry-picked miracle stories. Neither tells you what to actually expect. Here's a straight account of what improvement looks like before, during, and after a course of TMS. Measured, not hyped. What "Improvement" Actually Means Improvement in TMS isn't something we take your word for. It's tracked against a baseline using standard clinical scales. For depression, that's the PHQ-9; for anxiety, the GAD-7. You complete these at the start and at intervals through treatment, so change is measured rather than guessed at. There are two levels of improvement worth knowing, because they're different things: Response means your symptoms have at least halved from where they started. For most people who reach it, that's a meaningful, life-changing shift. Remission means you're no longer scoring in the depressed range at all. Not everyone reaches remission, and some people respond without fully remitting. Being clear about that distinction upfront is part of setting honest expectations. Before Treatment: Your Baseline The "before" picture is your baseline score, plus an honest conversation about what you're actually living with day to day: sleep, energy, motivation, the things depression or anxiety has been flattening. This matters more than it sounds. Depression distorts your memory of your own state. When you're in it, it's hard to recall feeling otherwise, and later it can be hard to appreciate how far you've come. A baseline score gives you and Dr. Clinch a fixed reference point, so improvement becomes something you can see on paper, not just try to sense.
Quick Answer: A first course of TMS that didn't deliver the relief you hoped for isn't the end of the road. The right next step depends on which situation you're in — TMS that worked and then faded, or TMS that never quite landed. Options range from a repeat course or maintenance sessions to changing the protocol itself, and for people who responded the first time, a repeat course works again in the large majority of cases. This post covers both paths honestly. Finishing a full course of TMS and not feeling the shift you were hoping for is discouraging, and it can feel like you've used up your last option. You haven't. "It didn't work" actually covers a few different outcomes, and each one points to a different, concrete next step. Knowing which one you're in is the first move. First, which kind of "didn't work" is this? Before talking about what to change, it helps to name what happened. Clinicians usually sort first-course outcomes into three groups: You responded, then slipped. Symptoms improved during or after treatment, then crept back weeks or months later. You partially responded. You felt some improvement, but not enough to call it a real change. You didn't respond. You completed the sessions and noticed little or no difference. Two terms come up a lot here. Response means a meaningful drop in symptoms - you feel noticeably better. Remission means your symptoms have largely resolved. A first course can produce a response without full remission, and that distinction shapes what comes next. If TMS worked and then faded: repeat courses and maintenance This is the most common version of "it didn't last," and it's also the most encouraging. Depression is a relapsing condition, and a fading response is not the same as TMS failing. For people who responded the first time and later relapsed, a repeat course tends to work again. Across published data, roughly 80–90% of patients who return for retreatment respond a second time , and one large multi-site study found about 84% of patients who needed another course or maintenance sessions improved again. Responding earlier and more strongly in your first course is associated with longer-lasting, more repeatable results. What is maintenance TMS? Instead of a full repeat course, some patients move to maintenance TMS — a lighter, individualized schedule of sessions (anywhere from weekly to monthly) designed to hold a good result in place. Maintenance is decided case by case, is billed per session (currently $75), and isn't covered by insurance. You can read more on our maintenance and retreatment blog and our pricing guide . If the first course didn't land: adjusting the protocol A second attempt shouldn't be a carbon copy of the first. If you saw little benefit, the useful question is what to change, and there's usually more to adjust than people realize. Re-mapping and coil positioning. Where the coil sits matters. A careful re-check of your treatment target and motor threshold can meaningfully change the dose your brain actually receives. Protocol and dose. Session count, pulse dose, and intensity can be revised. Some patients switch to or add iTBS (intermittent theta burst stimulation), a shorter session format, or an accelerated schedule that condenses treatment into a much smaller window. A longer or re-targeted course. Extending treatment or adjusting the target region is sometimes appropriate. None of this guarantees a different outcome, but it means a second round can be genuinely different from the first rather than a repeat of something that didn't help.

Quick Answer: A standard course of TMS takes weeks of daily visits, which makes traveling for it impractical. Accelerated and single-day (ONE-D) protocols compress that schedule into a few days, so out-of-state patients can complete treatment in a single trip. This guide covers why people travel, how the logistics work — flights, lodging, timing — and how we hand your care back to your provider at home. Most people don't think of depression treatment as something you'd travel for. TMS is the exception, and the reason is scheduling. A traditional course means showing up every weekday for weeks, which only works if the clinic is close to home. Compressed protocols change that math, and they're the main reason patients fly into Denver for care. Why would anyone travel for TMS? A standard TMS course runs 36 treatments over about nine weeks — five days a week for the first six weeks, then a taper. That's manageable if you live nearby and impossible if you don't. Accelerated protocols solve the scheduling problem by condensing that timeline into roughly a week, and single-day treatment compresses it further. When treatment fits into a few days, a plane ticket and a hotel become realistic, and patients start comparing clinics by specialization rather than by ZIP code. You can see how the accelerated model works on our accelerated TMS page . There's also an access reason. Not every city has a clinic that offers accelerated or single-day TMS, so patients in those areas either wait, settle, or travel to a clinic that focuses on it. Who tends to travel to us The patients who make the trip usually fall into a few groups: people whose local options don't include accelerated protocols, people who want relief in days rather than weeks, and people who have done their research and want a clinic that specializes in TMS specifically. Some travel a long way to do it — we've treated patients who came from as far as San Francisco for accelerated care. Traveling for treatment is a real commitment, so it tends to attract people who are motivated and have already tried the standard routes closer to home. Choosing between accelerated and single-day treatment Two compressed options make travel feasible, and which one fits depends on your history and your consultation. Accelerated TMS condenses a full course into about five days of treatment. ONE-D (single-day TMS) delivers 20 sessions across one to two days. Both require an initial consultation and mapping before treatment begins, and candidacy is decided clinically, not by preference. We'll walk you through which protocol suits your situation rather than defaulting to the fastest one. For what treatment costs and how self-pay and sliding-scale options work, see our pricing guide . Planning the trip: flights, timing, and lodging A few practical points make the trip smoother: Getting here. Our clinic is in Broomfield, between Denver and Boulder, and an easy drive from Denver International Airport. How long to stay. Plan for your treatment window plus a buffer day on each end - one to settle in before your first session, and one in case scheduling shifts. Your care team will confirm the exact number of days once your protocol is set. Where to stay. Book lodging close to the clinic so daily travel is short. Sessions are quick, but you may feel tired afterward, so a nearby base helps. Book flexibly. Until your consultation confirms you're a candidate, keep flights and hotels refundable where you can. A treatment day is usually short - patients are often in and out quickly - so you'll typically have time around your sessions, which is worth factoring into your plans.

TMS for OCD at Inspire TMS Denver: see our real clinic response and remission rates, how results are measured, and who the treatment fits.
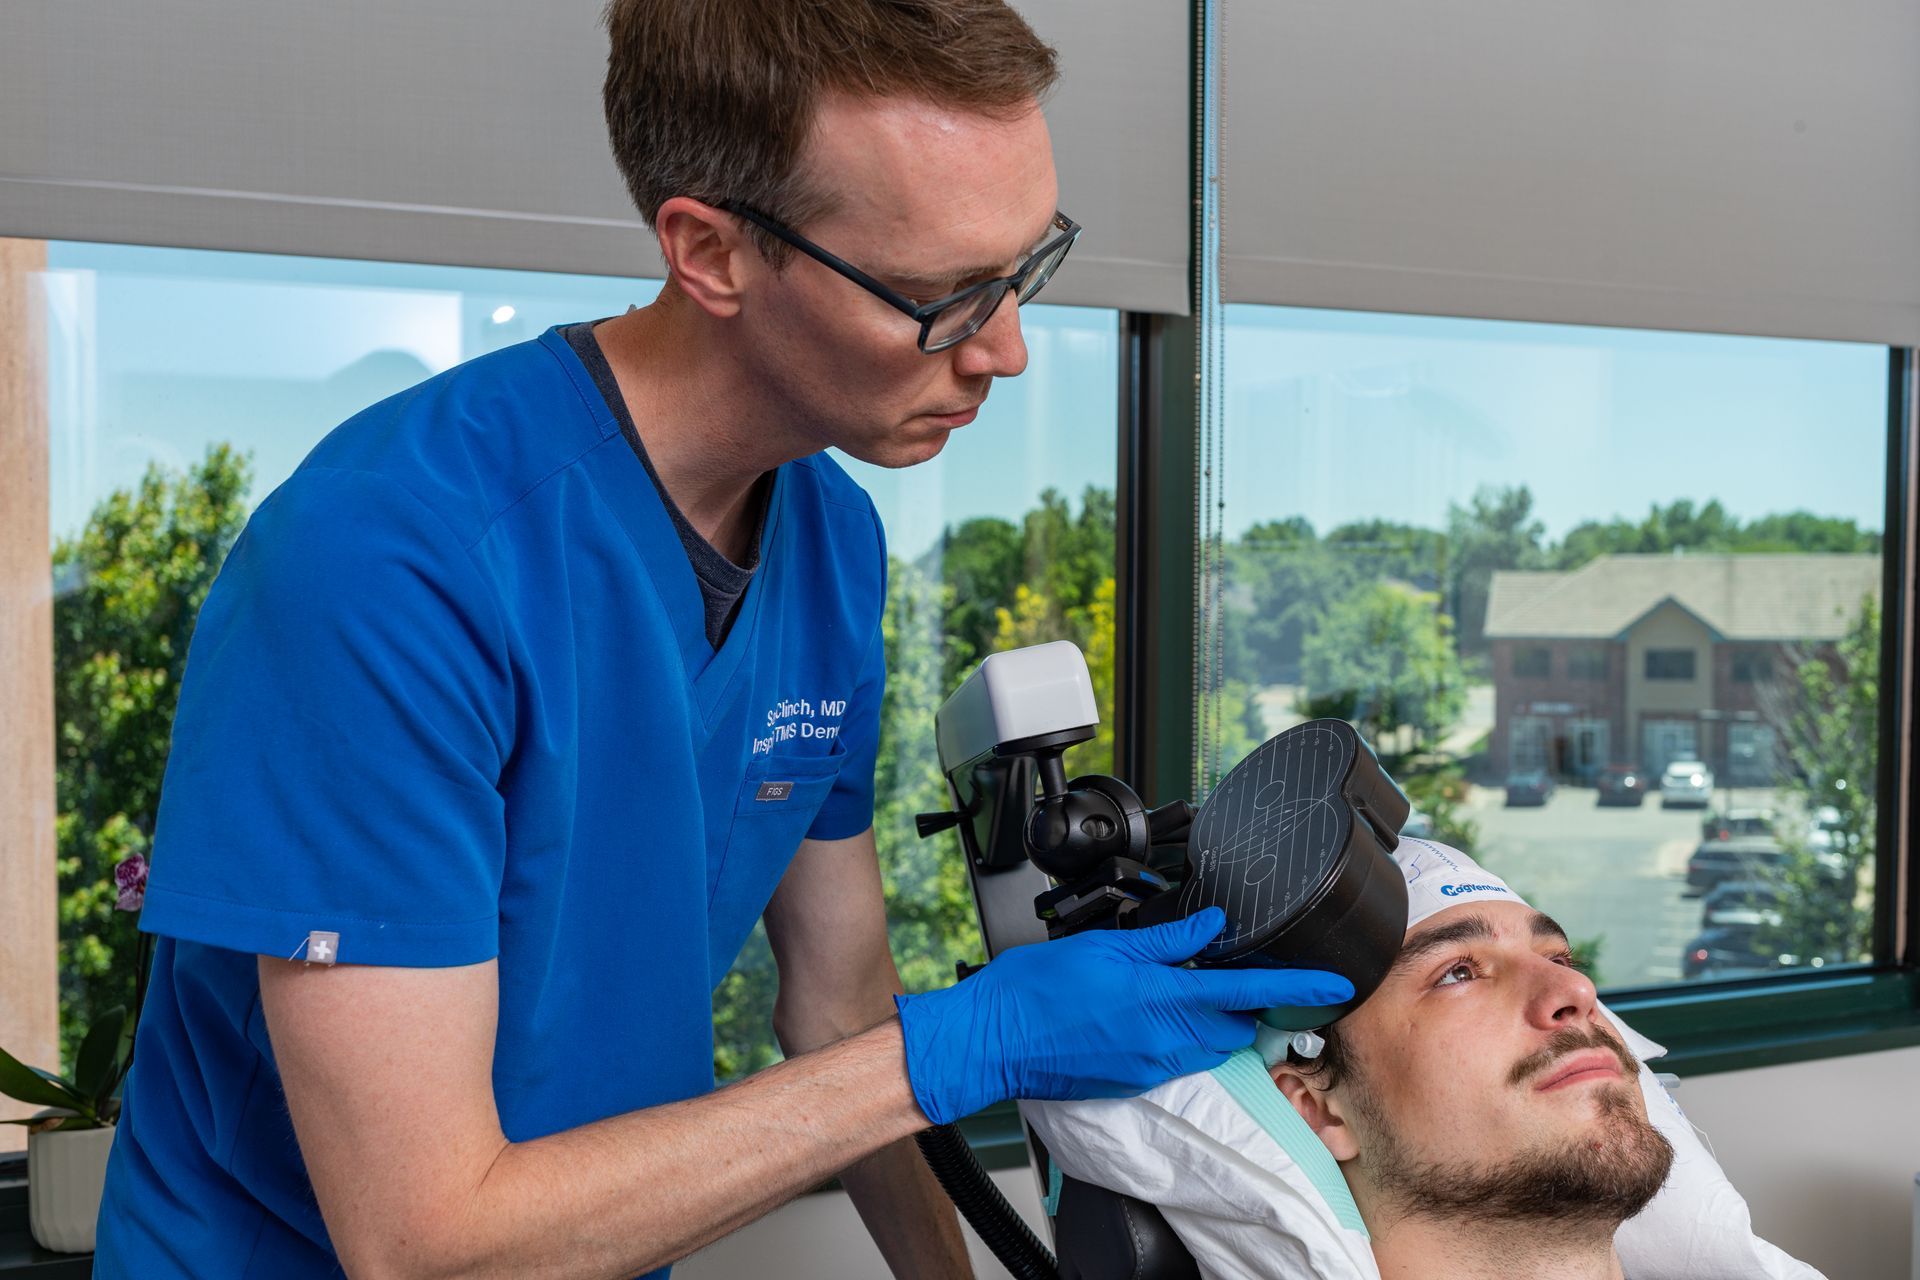
What does TMS actually feel like? A tapping sensation, no sedation, no pain like you'd fear. An honest walkthrough from first session to after.




